
The local hospital was profitable
Lincoln reported $157.106M operating revenue, $8.734M operating income, and a $9.903M total surplus in FY2024. Those are hospital results, not the maternity service-line P&L.
A profitable hospital can still close a low-volume service. The central public question is whether every workable staffing alternative was tested before moving births farther away.
Lincoln Hospital/Miles Campus plus MaineHealth parent context · Evidence through August 10, 2026
Start with control
Revenue is money coming in before costs. Operating income is what remains after operating costs. Net assets are assets minus liabilities. Keep the organization and year beside each number.
What matters
Lincoln reported $157.106M operating revenue, $8.734M operating income, and a $9.903M total surplus in FY2024. Those are hospital results, not the maternity service-line P&L.
For eight high-birth communities, the model increased birth-weighted town-center travel time by about 29.8 minutes when shifting from Lincoln to Mid Coast. Addresses, traffic, winter weather, islands, and EMS protocols can change the result.
MaineHealth advertised two OB/GYN float roles covering community delivery hospitals including Lincoln, with a $385,000 base salary. That proves a system mechanism, not that the positions were filled or sufficient.
MaineHealth cited no permanent OB/GYN hire since 2020, low volume, and unstable contracted coverage. The public record still lacks the service-line P&L, declined offers, locum invoices, and board alternatives model.
MaineHealth reports $3.172M in FY2024 340B savings for Lincoln. Acquisition cost, reimbursement, contract fees, actual fills, retained margin, and direct patient pass-through were not public.
The modeled $4.8M-$6.0M package combines permanent recruitment, internal rotations, locum blocks, and readiness-team retention. The midpoint is 2.8% of MaineHealth's FY2025 total excess, but clinical feasibility remains unproven.
MaineHealth cites low birth volume, recruitment difficulty and unstable contracted coverage.
Publish the alternatives model, actual recruitment offers and service-line costs behind the closure decision.
Look at the record




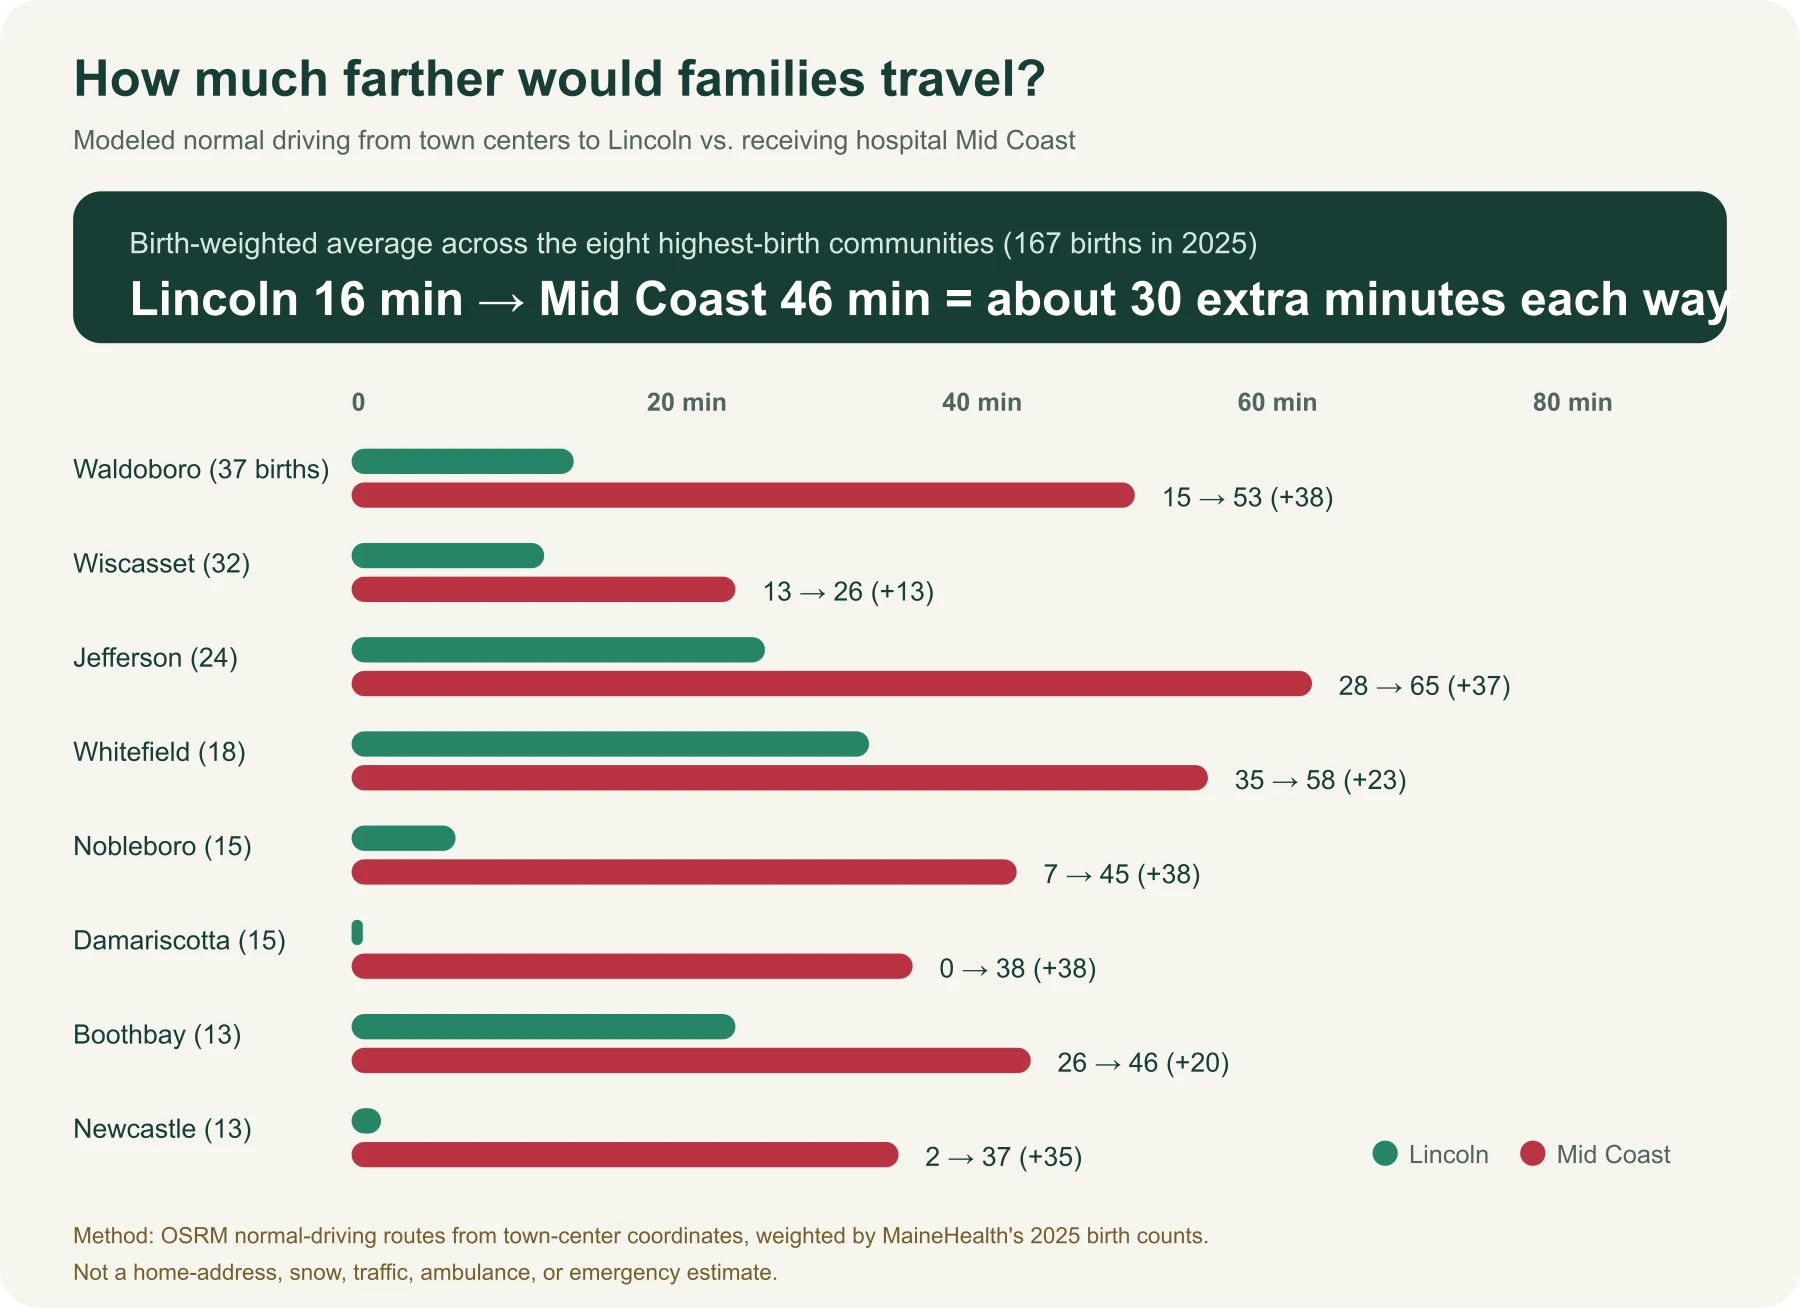

Travel model: sum(births in each town x travel minutes) / total births. Lincoln: 16.4 minutes; Mid Coast: 46.2 minutes; difference: 29.8 minutes across the 167-birth model population.
Budget midpoint: ($4.8M + $6.0M) / 2 = $5.4M. Compared with MaineHealth FY2025 total excess: $5.4M / $191.58M = 2.82%.
How it unfolded
MaineHealth says Lincoln last recruited a permanent full-time OB/GYN.
Lincoln recorded positive operating and total results.
Lincoln reported about 131 deliveries.
MaineHealth's board approved the regional model.
Inpatient deliveries are scheduled to transition to Mid Coast; prenatal/postpartum care is planned to remain local.
Check it yourself
Start with the visual PDF. Go deeper only where you want to. These files belong to this investigation, not a combined hospital report.
Earlier research editions retain their original dates; the visual reader above carries the August 27 compilation.
FY2024 · Lincoln Hospital · pp. 32-35, LincolnHealth
Supports: Revenue, expenses, surplus, cash, transfers, fund balance
Open source ↗FY2024-FY2025 · MaineHealth consolidated · Statements and liquidity note
Supports: Assets, cash, investments, operations, cash flow, grants
Open source ↗Updated Aug. 2026 · Lincoln/Mid Coast service · Assessment FAQ
Supports: Staffing rationale, delivery volume, transition date, board decision
Open source ↗2026 posting · MaineHealth delivery hospitals · Salary and locations
Supports: Two-role mechanism, base pay, covered hospitals
Open source ↗FY2024 / Aug. 2026 roster · Lincoln CAH201302-00 · Savings page and OPAIS roster
Supports: Participation, reported savings, sites and pharmacy arrangements
Open source ↗Cutoff 2026-08-10 · Lincoln and MaineHealth · Local file
Supports: Calculations, images, travel model and missing records
Open source ↗Published August 27, 2026. Historical records keep their original reporting periods. Read our methodology.